
Anti-Proteinase 3 antibodies (PR3-ANCA) are a significant biomarker in the Neutrophil Cytoplasmic Antibodies (ANCA) panel, primarily used in the diagnosis and management of certain autoimmune vasculitides, notably Granulomatosis with Polyangiitis (GPA).
What is Granulomatosis with Polyangiitis (GPA)?
Granulomatosis with Polyangiitis (GPA), formerly known as Wegener's Granulomatosis, is a rare autoimmune disease where the body's immune system mistakenly attacks its own blood vessels, causing inflammation. This inflammation primarily affects the respiratory system (like the sinuses, nose, trachea) and the kidneys, but it can involve other organs too. Symptoms can vary but often include nasal congestion, nosebleeds, cough, and kidney problems. If not treated, GPA can lead to organ damage. The exact cause of GPA is unknown, but treatment typically involves medications to suppress the immune system and reduce inflammation, helping to manage symptoms and prevent further damage to the organs.
What is Proteinase 3 and what are anti-PR3 antibodies?
Proteinase 3 is a serine protease enzyme predominantly located in the azurophilic granules of neutrophils and is involved in the degradation of extracellular matrix components, playing a key role in the innate immune response. The presence of anti-PR3 antibodies indicates an aberrant autoimmune response, wherein the immune system erroneously targets and attacks PR3, leading to inflammation and damage in blood vessels.
These antibodies are typically of the IgG class and are detected using techniques such as indirect immunofluorescence (IIF) and enzyme-linked immunosorbent assay (ELISA). In IIF, they usually show a cytoplasmic staining pattern (c-ANCA), reflecting their target location within neutrophils. The ELISA method provides a more specific and quantitative assessment of anti-PR3 antibodies.
Clinically, the detection of anti-PR3 antibodies is highly indicative of GPA, formerly known as Wegener's granulomatosis. Patients with GPA often present with high titers of these antibodies, and their levels have been correlated with disease activity, severity, and potential relapse. The presence of anti-PR3 antibodies is less common in other forms of vasculitis and can occasionally be observed in other autoimmune disorders, albeit less specifically.
Pathophysiologically, anti-PR3 antibodies are believed to contribute to the development of vasculitis by activating neutrophils, which in turn adhere to endothelial cells, release cytotoxic substances, and trigger a cascade of inflammatory responses leading to vessel wall damage. This process results in the characteristic features of vasculitis, such as vessel inflammation, necrosis, and granuloma formation.
Understanding the role and dynamics of anti-PR3 antibodies in GPA has not only been crucial for diagnostic purposes but also has significant therapeutic implications. It guides the use of immunosuppressive therapy and other targeted treatments to manage the autoimmune response and prevent disease progression. Continuous research and advancements in the understanding of these antibodies and their mechanisms of action are central to improving the diagnosis, monitoring, and treatment of autoimmune vasculitides.
 Anti Proteinase 3 Ab
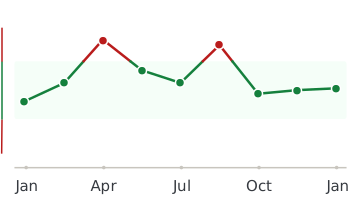
Every lab result you’ve ever had, charted and explained.
Healthmatters is a tracker for your lab results. Upload a report from any lab, any country — every marker charted and explained.
Start with my report →
All our content is backed by peer-reviewed studies, academic research, and trusted medical sources. We’re committed to accuracy and transparency — see our editorial policy for details.